|
Getting your Trinity Audio player ready...
|
Lung neuroendocrine tumours (NETs) can affect people in different ways. Some grow very slowly and may not cause symptoms at first, while others can cause symptoms related to the lungs or produce hormones that affect other parts of the body. Tests and scans can help your healthcare team understand your individual cancer and plan the most appropriate treatment and follow-up care.
This page explains more about lung NETs, including how they develop, possible symptoms, how they are diagnosed and monitored, and the treatments you may be offered. It also includes information about living with a lung NET, follow-up care, taking an active part in your care, and where you can find further information and support.
Use the links in the box to find the information that is most relevant to you.
What is a neuroendocrine tumour (NET)?
Neuroendocrine cancer is a type of cancer that begins in the neuroendocrine cells, which are found throughout the body. These cells have the ability to release hormones that can regulate many body functions. When they become cancerous, their growth rate and normal function is disrupted.
There are two main types:
- Neuroendocrine tumours (NETs) – usually slower growing
- Neuroendocrine carcinomas (NECs) – less common and faster growing
This page focuses on lung NETs (also called lung carcinoids).
Your lungs
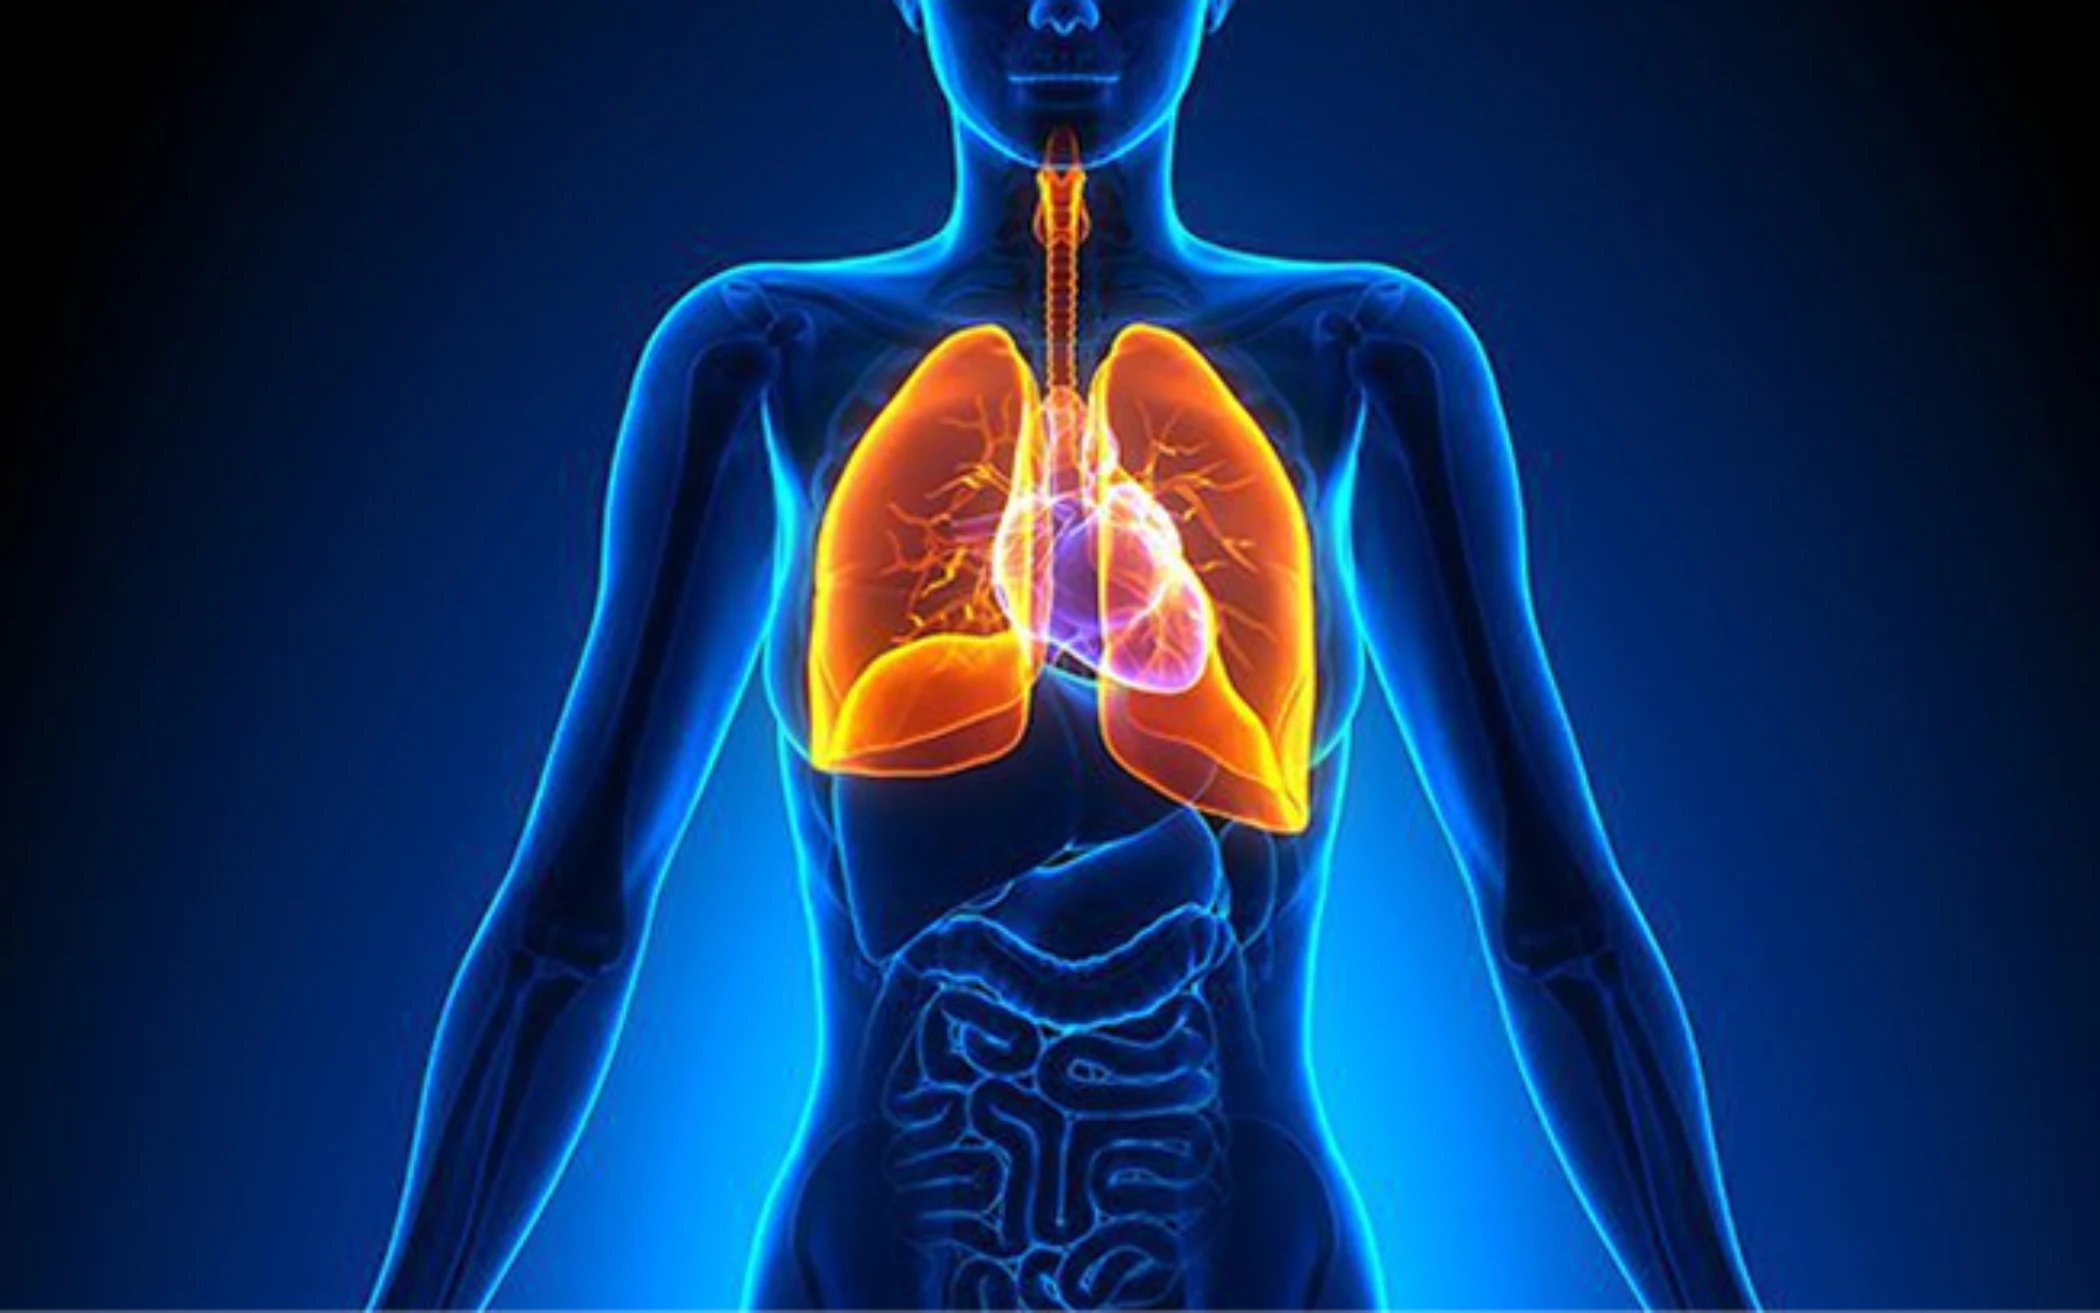
Your lungs sit in your chest on either side of your heart.
Each lung is divided into sections, called lobes:
- The right lung has three lobes: upper, middle and lower
- The left lung is slightly smaller and has two lobes: upper and lower
Each lobe is further divided into smaller areas, known as segments.
The lungs are covered by a thin protective layer called the pleura.
There is a small amount of fluid between the lungs and the chest wall; this allows the lungs to move smoothly as you breathe in and out.
Lung size varies from person to person. On average, men tend to have slightly larger lungs than women. Even during exercise, we usually use only about 70% of our full lung capacity.
Lungs help you breathe by:
- Taking in oxygen
- Removing carbon dioxide
They can also:
- Help protect against infection
- Filter blood
- Support hormone and chemical balance
How do lung NETs develop?
For most people, there is no clear cause of lung NETs.
Lung NETs are usually not inherited. Rarely, they may be linked to a genetic condition called MEN1. Less than 5% (1 in 20) of people with MEN1 develop a lung NET.
Further information on MEN1 can be found at AMEND.
A related condition: diffuse idiopathic pulmonary neuroendocrine cell hyperplasia (DIPNECH)
This is a rare, non-cancerous lung condition. It may slightly increase the chance of developing a lung NET. It is often slow growing and manageable with monitoring.
The exact cause of DIPNECH is not yet known, and doctors are still learning how it develops. It can occur in otherwise healthy lungs and is not linked to smoking.
It most often affects women in middle age or later life, many of whom have never smoked.
Signs and symptoms
Some people have no symptoms at first.
When symptoms occur, they may include:
- Shortness of breath
- Persistent cough or wheeze
- Chest pain
- Recurrent chest infections
- Sputum (phlegm) may be blood stained
- Persistent tiredness or lack of energy
- Loss of appetite or unexplained weight loss
Hormone-related syndromes
Up to 5% (1 in 20 people) who have a lung NET may present with or develop ‘carcinoid syndrome’, with symptoms such as:
- Dry flushing (primarily on the face/neck – but it can spread body wide)
- Diarrhoea
- Wheezing
- Fast heartbeat
Other symptoms may also occur, but rarely. These include night sweats and/or allergy-like symptoms, such as itchy/irritated skin, watery eyes/runny nose (rhinitis), and/or swelling of the salivary glands.
Up to 2% (2 in 100 people) may present with or develop Cushing’s syndrome, with symptoms such as:
- Weight gain
- High blood pressure
- Diabetes
- Tiredness/fatigue
- Excess hair growth on the face, chest, abdomen or thighs
- Changes in vision
Tell your healthcare team about any new or changing symptoms.
Carcinoid crisis (rare) may occur in those who have carcinoid syndrome
Carcinoid crisis can happen during anaesthesia or tumour manipulation (biopsy, surgery or interventional radiology – e.g. embolisation or ablation treatments) or be triggered by mental/physical stress.
Symptoms may be similar to carcinoid syndrome but are much more severe. These include severe flushing – often accompanied by palpitations or a fast, irregular heart rate, low blood pressure, confusion and breathing difficulty – and can be life-threatening.
Specialist teams plan care to reduce this risk.
If you are at risk of carcinoid crisis, carry a Carcinoid Crisis Card so healthcare professionals know how to manage your care in an emergency. You can order one from us for free.
Adrenal insufficiency and adrenal crisis
One treatment for Cushing’s syndrome is to remove one or both adrenal glands. If you have had this treatment you may be at risk of adrenal insufficiency with or without adrenal crisis.
Adrenal insufficiency means the body cannot make enough steroid hormones, which are vital during illness or stress. If not treated quickly, this can lead to an adrenal crisis, which is a medical emergency. Risk increases during illness, surgery, injury, or vomiting/diarrhoea: follow ‘sick day’ rules.
Specialist teams plan care to reduce this risk.
Always carry a Steroid Emergency Card if advised. You can order one from The Addison’s Disease Self-Help Group, or download here.
Rare symptoms (paraneoplastic syndromes)
Very rarely, cancer can trigger symptoms caused by the body’s immune response to cancer.
These are uncommon but can sometimes cause serious health problems.
Watch our video: Paraneoplastic Syndromes – Explained
Symptoms related to treatment
Treatments can cause side effects, but not everyone experiences them.
Your team will talk through possible side effects and how they can be managed.
Tests and scans
Blood and urine tests
- Chromogranin A (CgA) +/- chromogranin B (CgB)
- 5-HIAA or serotonin
- NT-ProBNP may be taken if you have a history of heart disease or carcinoid syndrome
- Vitamin, mineral and trace element check
If Cushing’s syndrome is present or suspected: serum cortisol, urinary cortisol and adrenocorticotropic hormone (ACTH) may be tested.
If multiple endocrine neoplasia type 1 (MEN1) is present or suspected: calcium and parathyroid hormone (PTH) may be tested, and you may be asked to consider genetic studies (if not already undertaken).
Scans and procedures
- Bronchoscopy or endobronchial ultrasound (EBUS)
- Chest X-ray, CT, MRI scans
- Gallium-68 PET-CT scan (or Octreoscan)
- A FDG-PET scan may also be requested if you have a high grade 2 or grade 3 lung NET
- Echocardiogram (if you have a history of heart disease or carcinoid syndrome)
- Biopsy (tissue sample)
Watch our video: Your Guide to Scans
For neuroendocrine cancers of the lungs, there are different ways samples may be taken, depending on your situation.
If you have surgery as your first treatment, any tissue removed will be sent for testing (histopathology). If surgery is not possible, or more information is needed, a biopsy may be done. This involves taking a small tissue sample to examine under a microscope.
Sometimes, a bronchoscopy with lavage is used. A thin tube is passed into the lungs and a small area is gently washed with fluid, which is then collected and checked for abnormal cells.
In some cases, video-assisted thoracoscopic surgery (VATS) may be used. This is a type of keyhole surgery that allows doctors to look inside the chest and take samples through small cuts.
These tests help confirm diagnosis and guide treatment.
Treatments
Your care is individualised based on your tumour, health and preferences.
1. Monitoring (surveillance)
Some lung NETs do not need immediate treatment. Regular scans and check-ups help monitor changes.
2. Surgery
If possible, surgery aims to remove the tumour. Types range from removing a small section to a full lung:
- Metastectomy, which involves a small lung tumour being ‘scooped’ out of the lung. This can be done for a very small isolated primary lung NET but is usually undertaken to remove metastatic tumours.
- Wedge resection, which involves the removal of a ‘wedge’ of lung that contains the tumour.
- Segmentectomy, which involves the removal of the segment(s) of lung that contains the tumour.
- Lobectomy, which involves the removal of one or more lobes.
- Sleeve resection, which involves the removal of an upper lobe along with part of the main airway. The remaining lung is then attached to the remaining airway.
- Pneumonectomy, which involves the removal of an entire lung.
Watch our video: Lung Surgery – why it’s performed, what to expect and tips for recovery
3. Non-surgical treatments
Non-surgical treatments may include:
- Somatostatin analogues (SSAs): to control hormone-related symptoms and/or tumour growth.
- Targeted therapy (e.g. everolimus): this is a targeted treatment called an mTOR inhibitor. It works by blocking a protein that helps some cancer cells grow and form new blood vessels; this can slow or stop tumour growth. It is currently approved by the National Institute for Health and Care Excellence (NICE) only for non-functioning lung NETs, so it is not usually available for people with carcinoid syndrome (functioning NETs).
- Chemotherapy: is rarely used as a first treatment for low grade (G1-2) lung NETs but may be considered in G2-3 or if other treatments are not suitable or have stopped working. It may be given as tablets or through a drip into a vein. For example CapTem (capecitabine + temozolomide) tablets or rarely, Streptozocin/5FU via a drip.
- Radiotherapy: external beam radiation therapy (EBRT) may be used to target specific solitary small lung NETs or treat symptomatic bone metastases. Stereotactic body radiation therapy (SBRT) may be used to treat early-stage inoperable cases.
- Radioligand therapy (RLT, also known as peptide receptor radionuclide therapy (PRRT) or lutetium‑177): a targeted internal radiation treatment. It delivers radiation directly to cancer cells, usually given in four sessions spaced 8–12 weeks apart. It is mainly used for metastatic or progressing disease. At present, RLT does not have NICE approval for lung NETs but may be available through clinical trials or other funding routes.
- Symptom control and supportive care: includes any treatment or support that helps you feel better, even if it is not directly treating the cancer. This may include medicines, dietary advice and/or psychological support. Techniques such as mindfulness or relaxation may help with pain, fatigue, stress or anxiety.
- Clinical trial therapy: clinical trials are used to find out if new treatments and techniques are safer and more effective than the ones that already exist, or for discovering if existing treatments can be used in different, more effective, ways or combinations.
Diagnosis and living with lung NET
A diagnosis of neuroendocrine cancer can bring questions, uncertainty and a range of emotions. Information and support are available to help you understand your diagnosis and navigate what happens next.
Just diagnosed with neuroendocrine cancer? Access information and support to help you navigate the early days after diagnosis.
Follow-up care
Follow-up is an important part of your ongoing care. It helps your healthcare team check how you are doing, spot any changes early, and support your physical and emotional wellbeing.
While expert guidelines offer a general plan for follow-up, your care will always be tailored to you and your specific type of neuroendocrine cancer.
At each appointment, your team will ask how you are feeling, review your symptoms and medications, and arrange blood tests if needed.
You may also be offered a holistic needs assessment (HNA). This is an opportunity to talk with your specialist nurse or doctor about any physical, emotional, practical or social needs, so the right support can be put in place.
Guideline follow-up recommendations
Typical carcinoids (grade 1 and low grade 2 NETs)
If surgery was possible and thought to be curative:
- Every 6 to 12 months for the first 2 years
- Then every 2 to 3 years for up to 10 years
- Then every 3 to 5 years after that
If surgery was not possible or not complete:
- Usually every 3 months at first
- This may be spaced out to every 6 to 12 months if scans and symptoms remain stable
Atypical and supracarcinoid (higher grade 2 and grade 3 NETs)
If surgery was possible and thought to be curative:
- At 3 months after surgery
- Then every 6 to 12 months for 5 years
- Then every 1 to 2 years for up to 10 years
- Then every 2 to 5 years after that
If surgery was not possible or not complete:
- Usually every 3 months at first
- This may be extended to every 6 to 12 months if there are no signs the cancer is growing or changing
At or before each clinical review, you may have a contrast‑enhanced CT scan of the chest, abdomen and pelvis or a CT scan of the chest plus an MRI scan of the abdomen.
You may also have a Gallium‑Dotatate PET scan at 3 to 6 months (if it wasn’t done at diagnosis) and further Gallium‑Dotatate PET scans every 1 to 2 years, but only if clinically needed.
If you have a higher grade 2 or grade 3 lung NET and a previous FDG‑PET scan has provided clearer information, your team may choose to use this instead of, or alongside, a Gallium‑Dotatate PET scan, if clinically appropriate.
A bronchoscopy will usually only be offered if it is clinically needed and the tumour could be seen by bronchoscopy when you were first diagnosed
How you can be part of your care
You are a key part of your team. You can help by:
- Reporting new symptoms or any changes in current symptoms or overall health
- Asking questions if at all uncertain or you want more information about your diagnosis and/or plan of care
- Attending appointments made – and checking up with the team if you haven’t received an appointment according to your agreed plan of care
Support and further information
We have worked with the International Neuroendocrine Cancer Alliance (INCA) to provide resources in more than 10 different languages: these are available here.
Stories from our community
Watch: Radiology and Lung Neuroendocrine Tumours – Dr Thomas Westwood
Hear from more people connected to neuroendocrine cancer as they share their experiences, perspectives and insights – from living with the condition to caring for, treating and supporting those affected.
Remember
Remember: every person’s experience with lung NET is different – there may be shared similarities, but each journey is unique.
Your healthcare team will support you every step of the way, guiding your treatment, care, and follow-up. We’re here alongside them, offering additional support and information whenever you need it.
The information on this page is based on available clinical expert guidelines and publications. It is for informational purposes only and should not be considered professional medical advice.