|
Getting your Trinity Audio player ready...
|
Neuroendocrine cancer of the testes is very rare and can affect people in different ways. It may cause symptoms such as a lump, swelling or discomfort in a testicle, but is often diagnosed during investigations or surgery for suspected testicular cancer.
Tests and scans can help your healthcare team understand the type of cancer, whether it has spread and which treatments may be appropriate.
This page explains more about neuroendocrine cancer of the testes, including possible causes and symptoms, how it is diagnosed and monitored, and the treatments you may be offered. It also includes information about living with the condition, follow-up care and finding support.
Use the links in the box to find the information that is most relevant to you.
What is neuroendocrine cancer?
Neuroendocrine cancer is a type of cancer that begins in the neuroendocrine cells, which are found throughout the body. These cells have the ability to release hormones that can regulate many body functions. When they become cancerous, their growth rate and normal function is disrupted.
This page looks at neuroendocrine cancer of the testes.
Neuroendocrine cancer of the testes
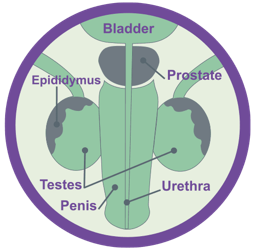
The testicles are two oval-shaped glands that sit within the scrotal sac, just below the penis. It’s quite normal for one testicle to be slightly larger than the other, although the size and shape should be roughly the same. It can also be normal for one to hang a bit lower than the other.
The testicles contain structures called seminiferous tubules, which produce cells called germ cells. These in turn produce sperm. The sperm move into the epididymis (a tube running behind the testicle) where they mature. They get stored there for a few weeks and combine with fluids from other areas (the prostate and seminal vesicles) to form semen. The testes are also responsible for producing several hormones – the key one being testosterone (the male sex hormone).
Testosterone helps regulate certain male characteristics – such as body and facial hair, depth and sound of voice, muscle development, weight, the ability to have an erection, ‘sex drive’ (libido), energy and stamina – as well as influencing mood and wellbeing.
Neuroendocrine cancer of the testes accounts for less than 1% of all testicular tumours and can be divided into three subtypes:
- Primary testicular neuroendocrine cancer (approximately 76%)
- Secondary neuroendocrine cancer of the testes (approximately 6%)
- Those associated with testicular teratoma.
Subtype 3 should be considered separately to 1 and 2, as care and outcome is different. Subtype 3 is more similar to testicular teratoma (a germ-cell type of testicular cancer). Germ cell tumours are by far the most common testicular tumours.
Causes and risk factors
We do not know exactly what causes neuroendocrine cancer of the testes, however it is important to follow advice in leading a healthy lifestyle: eat healthily, exercise and avoid smoking and too much alcohol.
Most neuroendocrine cancers do not run in families; however, a number of rare conditions may increase the risk of them developing. Therefore, if other members of the family have been diagnosed with cancer, or have a known genetic condition, it is important that you tell your specialist team about not only your personal medical history, but also any family medical illnesses or conditions.
We recommend speaking to your GP, and specialist team, if cancer runs in your family. They may refer you for an NHS genetic test, depending on whether a test is available, which will tell you if you have inherited one of the cancer-risk genes.
Neuroendocrine cancer of the testes is rare – and may not be associated with the above mentioned genetic alterations or family history. However, if you do have a genetic alteration or strong family history, knowing this information may help your specialist team in planning your care and ensuring follow up is appropriate for you.
Symptoms
Diagnosis of neuroendocrine cancer of the testes usually occurs during investigations (or following surgery) for testicular cancer, therefore signs and symptoms, if present, will be similar:
- A lump on or swelling of the testicle
- A dull ache, dragging sensation or swelling in the scrotum
- Altered sensation, pain or discomfort in a testicle or the scrotum
- A dull ache or pain in the groin, abdomen or back
- Breast tenderness or swelling (gynecomastia) is rare but may occur
Around 96% of abnormal testicular conditions (lumps and bumps) will not be cancerous.
Carcinoid syndrome is a very rare occurrence. It is associated with either primary testicular neuroendocrine cancer that has spread to the liver (less than 3%) or as symptoms already present in those for whom testicular disease started elsewhere.
Other, rarer symptoms, including paraneoplastic syndrome and oncological emergencies (a specific set of health concerns that can occur in any cancer), such as raised calcium levels (hypercalcaemia), may occur.
Tests
Tests that may be used for the diagnosis and/or monitoring of neuroendocrine cancer of the testes:
Blood and urine
- Full blood count
- Liver and kidney function
- Chromogranin-A
- Urinary 5-HIAA
- αFP, HCG, LDH
Note that usual markers for testicular cancer are often negative. Neuroendocrine cancer markers may be positive.
- Testosterone, LH, FSH and semen analysis: consider fertility counselling including sperm banking
- Mid-stream urine sample
- Clinical examination of testes
Scans and other tests
- Testicular ultrasound with or without biopsy
- CT of the chest/abdomen/pelvis
- MRI of the pelvis with or without spine
- Bone scintigraphy (if bone involvement suspected)
- Gallium-Dotatate PET/CT (SRS SPECT/CT if Dotatate PET not available)
- FDG-PET if high grade or rapidly progressing disease
Watch our video: Your Guide to Scans
Pathology (what can be seen through special tests under a microscope)
- Differentiation and cellular morphology
- Synaptophysin
- Chromogranin
- Ki67
- Assessment for teratoma or germ cell components
Treatment options
The key aim of treatment should be to help you have the best possible care and quality of life, by ensuring access to appropriate treatment, management of symptoms and addressing what’s most important to you.
Treatment options will depend on the type, position and size of your cancer – and whether (and to where) it has spread.
It will also depend on whether you have any other health concerns and/or illnesses and your general health and fitness.
One or more of the approaches below may be suggested:
- Surgery
- Control of your disease, by slowing or stopping further growth and/or spread
- Palliation, or easing, of any symptoms you may be experiencing
Surveillance
Monitoring through clinic review, bloods and scans can be used to assess how well treatment is working or in periods between treatments (which may be months or years).
As not everyone will need to be on treatment, surveillance can be used to check your cancer and general health for any signs of change that may mean that a treatment might need to be considered. All treatments have possible side effects, therefore, it is important to know when treatment may be helpful for you or not.
Surgery
To remove, partially remove or bypass neuroendocrine cancer and/or secondary sites of disease (metastases).
Orchidectomy
Removal of a testicle (if only one is removed, the remaining testicle should be able to continue to produce testosterone – however if surgery would leave you without testicles you may require testosterone replacement therapy).
Retroperitoneal lymph node dissection (RPLND)
If there are any signs of potential cancer beyond the testicle, such as enlarged lymph nodes in the abdomen, it may be suggested that men undergo this procedure. This type of surgery carries a low risk of affecting fertility (may make it more difficult for men to father a child), however, it should have no physical effect on a man’s ability to get and maintain an erection.
Non-surgical treatments
- Somatostatin analogues (SSAs): can be used to help regulate the secretion of hormones if abnormal levels are being produced. SSAs may also be used to slow down growth rate in low to moderate grade ‘well-differentiated’ neuroendocrine cancer (NET).
- Chemotherapy: can be given orally (in tablets) or intravenously (through a vein) to slow tumour growth or try to reduce tumour size. This may be the first line therapy in high grade disease – particularly ‘poorly-differentiated’ neuroendocrine carcinomas or in combination with other treatments. Chemotherapy may also be used to increase tumour cell sensitivity to radiation therapies.
- Targeted molecular therapies: can be given orally (in tablets) or intravenously (through a vein) to slow tumour growth or try to reduce tumour size.
- Peptide receptor radionuclide therapy (PRRT, also called radioligand therapy): uses targeted radiation to treat neuroendocrine cancer cells. Can be used in some patients who have had a ‘positive’ Octeotide or Gallium scan (‘receptor positive’ disease).
- Radiotherapy: is sometimes given after surgery to kill any cancer cells that might remain there. It may also be used for cancer that has spread beyond the primary site, in particular if disease has spread to the bones – here it is used to help control growth of any spread and alleviate bone pain.
- Interventional radiology: through techniques such as embolisation or ablation, this can be used to treat neuroendocrine cancer that develops in the the liver and/or lung(s).
- Clinical trials: clinical research and safe new treatment development is essential to provide best care for those with neuroendocrine cancer – we need to know that treatments not only work but work safely. There are several phases of trial therapy. Each trial has specific criteria in regards to patient suitability – this can be discussed with your clinical team. You do not have take part in a trial – participation is voluntary.
- Symptom control: managing symptoms, including pain, is an important part of total care – and therefore occurs throughout care, not just at ‘end-of-life’. Symptom control or ‘palliation’ refers to what is used to alleviate or reduce the impact your cancer, other health issues and/or treatments may be having on you and your physical and mental health. It can include anything from simple medication and/or a combination of some of the treatments mentioned above to counselling and practical support.
Diagnosis and living with neuroendocrine cancer of the testes
A diagnosis of neuroendocrine cancer can bring questions, uncertainty and a range of emotions. Information and support are available to help you understand your diagnosis and navigate what happens next.
Just diagnosed with neuroendocrine cancer? Access information and support to help you navigate the early days after diagnosis.
Follow-up
There are expert agreed guidelines regarding how and when follow up should occur, however, in practice this varies and often with good reason. Follow up should be expert informed and evidence/research based but also tailored to you and what is appropriate for your best care.
However, given the rarity of testicular neuroendocrine cancer there are no consensus guidelines on follow up – however one can utilise guidelines for testicular cancer follow up (and reliability of neuroendocrine cancer markers also help in informing surveillance/follow up):
- Physical exam and biochemical markers 3–4 monthly for first 2 years, then 6–12 monthly to annually
- CT at 3 months, 9 months then 6–12 monthly (MRI can replace CT depending on patient status).
Functional imaging (e.g. Gallium-Dotatate PET/CT (SRS SPECT/CT if Dotatate PET is not available) with or without biopsy may be indicated in recurrent/progressive disease.
Further imaging as clinically indicated, e.g. CT chest.
Advanced disease
Follow up should be aligned with guidelines, and also guided by prognosis, expected treatment efficacy and treatment related toxicity. Your health, wellbeing, physical activity, informed choice, preference for ongoing care, and your aim of treatment should be reviewed and discussed to best plan your care.
Stories from our community
Hear from people connected to neuroendocrine cancer as they share their experiences, perspectives and insights – from living with the condition to caring for, treating and supporting those affected.
Remember
Remember: every person’s experience with neuroendocrine cancers of the testes is different – there may be shared similarities, but each journey is unique.
Your healthcare team will support you every step of the way, guiding your treatment, care, and follow-up. We’re here alongside them, offering additional support and information whenever you need it.
The information on this page is based on available clinical expert guidelines and publications. It is for informational purposes only and should not be considered professional medical advice.